Diagnostic Use
Therapeutic drug monitoring is not necessary to guide routine paracetamol use for fever or pain control. However, plasma/serum paracetamol concentration should be used to assess the need for acetylcysteine administration in all patients presenting with deliberate self-poisoning with paracetamol, regardless of the stated dose.
The minimum time for assessment of levels after ingestion is 4 hours. Beware of incomplete absorption prior to 4 hours post ingestion. Specimens collected earlier than 4 hours may not indicate the peak serum concentration.
The nomogram below can only be used in acute immediate release paracetamol ingestions with a known time of ingestion. In case of acute modified release paracetamol ingestion or repeated supratherapeutic ingestion, different management protocol/flow chart should apply – refer to your local centre for most up-to-date information.
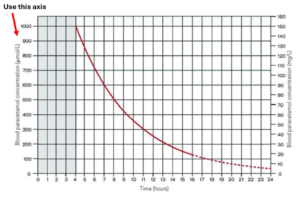
NOTE:
– Treat patients with paracetamol concentrations on or above the nomogram treatment line with acetylcysteine infusion (see local protocol).
– Massive paracetamol overdoses that result in high paracetamol concentrations more than double the nomogram line are at increased risk of acute liver injury and may benefit from an increased dose of acetylcysteine. Consult local protocol/management flow chart. A paracetamol concentration should also be repeated.
Interpretation
Refer to the nomogram below under ‘Diagnostic Use’ (used by the National Poisons Centre, Dunedin, NZ):
- The time is hours since ingestion.
- The units are umol/L.
- Patients with drug concentrations above the line should be treated.
- Patients with risk factors for toxicity (e.g. alcoholism, enzyme inducing drugs, fasting) may need treatment if the drug concentration is above the dotted line.
Additional caution is required in presentations of staggered or chronic overdoses and when slow-release tablets were ingested.
Jaundiced patients (bilirubin >500 umol/L) may show false-positive serum paracetamol results.
Paracetamol toxicity or N-acetycysteine can negatively interfere with lactate, urate, total cholesterol, HDL-cholesterol and triglyceride assays. Exercise caution in interpreting these results.
Test Method
Principle: Homogeneous enzyme immunoassay
Analysers: Roche Diagnostics Cobas c503
Reagents: ACET2